The 10 Lessons
The interesting and informative aspects that I discovered will be emphasized in the upcoming days beneath each lesson. The chapters do not entirely align with the 10 lessons.
Lesson One (Chapter 1: From Tragedy to Opportunity)
In reality, the organized human capacity to utilize that knowledge has exceeded our remarkable scientific understanding by a significant margin. Regarding our remarkable scientific knowledge, the Covid conflict serves as a narrative.
The required mindset to respond to the Covid pandemic is a challenge that we, as individuals, face in fighting a war-like treatment.
The United States did not have a war mindset.Output: The United States did not possess a mindset focused on war.Input: We were not prepared, and we did not respond with the urgency of fighting a war against a novel microbial threat.Output: Our lack of preparedness and failure to respond urgently mirrored the approach needed to combat a new microbial threat.Input: We had the knowledge–what we should do, but lacked how we should do it.Output: Although we possessed the necessary knowledge about what actions to take, we were unsure about the appropriate methods to implement.Input: And we lacked the national leadership in 2020 to ensure we tackle the four challenges.Output: Additionally, in 2020, we faced a deficiency in national leadership that hindered our ability to effectively address the four challenges.
Why? There are three primary cultures in administration:.
“The task in the Covid battle, as in any significant crisis, is to blend all these societies in implementation.”
The war on Covid has exposed a national collective incompetence in governance. The leaders of the United States could not effectively apply their vast country’s assets enough. Trust and confidence in the government, which were already low, have been further eroded. The most successful national program, Operation Warp Speed, ended up being substantially run by the Department of Defense, which distributed and produced vaccines at a warp speed to wage the war.
My perspective: Overall, I concur.
Lesson Two (Chapter 3: The Defenders.)
The United States faced the 21st century pandemic with infrastructure primarily constructed to address issues of the 19th century.
The Centers for Disease Control and Prevention have well-documented the threats to infrastructure in the 21st century, as well as the decades of underinvestment in health departments. And it’s true that an infection novel can spread quickly in one part of the world, affecting several continents. Yes, it is absolutely true that the world is now more connected than ever through international travel.
The United States requires a fresh “National Health Security Enterprise” that offers “strategic-level governance” over, at minimum, the subsequent:.
The issues identified consist of:
Similar to our preparations for a conflict, the recently proposed “National Health Security Enterprise” aims to allocate resources to readiness and revamp these partnerships while envisioning new possibilities.
Lesson Three (in Chapter 6, p. 156: Communities Adapt with Limited Resources.)
Partisan divisions regarding America’s response to the Covid pandemic were partially due to policy failure, rather than being the root cause.
Instead, we found that the main obstacle to protecting citizens and ensuring competence was not failures and incompetence, but rather the toxic politics that further divided the country in times of crisis. Resorting to blunt instruments and flying blind, including failures in federal executive leadership and policy, resulted in bad outcomes.
Lesson Four (Chapter 2, pp. 27–28: Origins, Prevention, and Ca)
Looking ahead, two significant objectives are propelled by existing knowledge. When considering any hypothesis regarding the emergence of SARS-CoV-2, reaching a conclusion becomes challenging in the absence of sufficient evidence accessible within China.
This was one of my preferred sections. It was highly reflective and methodical.
How was SARS-CoV-2 transmitted to the human population
In conclusion, there is not enough proof to confidently determine which of these theories is the probable causal explanation.
What steps can we take to enhance ourselves for the future?
First and foremost, we believe that governments must improve their intelligence to enhance their awareness of the ongoing situation. In the past, national governments like China relied on a system that failed decisively to provide timely reporting of what was happening. We need an alternative system that can meet our needs.
In order to oversee the most risky research, we suggest a significant and demanding international undertaking. The emphasis of the research should cover both dual-purpose worries and biological security, with bio-safety being a crucial component.
Lesson Five (Chapters 4 and 5: Failure of containment; Delay in & The collapse of the Federal Crisis Management leads to the commencement of Operation)
Page 113 provides a summary of three important matters. February witnessed the mobilization of certain countries while the United States refrained from doing so. The month of January 2020, described as a period of alerts and initial responses, is documented in Chapter 4, which focuses on the initial months of 2020.
Influenza or SARS-1 served as the conceptual framework. The United States failed to anticipate an airborne communicable respiratory pathogen with a significant number of asymptomatic cases and covert transmission.
Biomedical monitoring:
Testing: pending.
Lesson Six (Chapter 7: The Healthcare System Weakens.)
The uniquely fragmented healthcare system in America is unable to adequately respond to the urgent need for national enterprise security health.
“The economics of healthcare in America discourage investment in preparedness
Lesson Seven (Chapter 9: Combating with Medications and Vaccinations.)
National security should be considered when evaluating and coordinating investments in health security, including therapeutics and vaccines. Health security is a component of national security.
Lesson Eight (Chapter 10: Global War Strategy.)
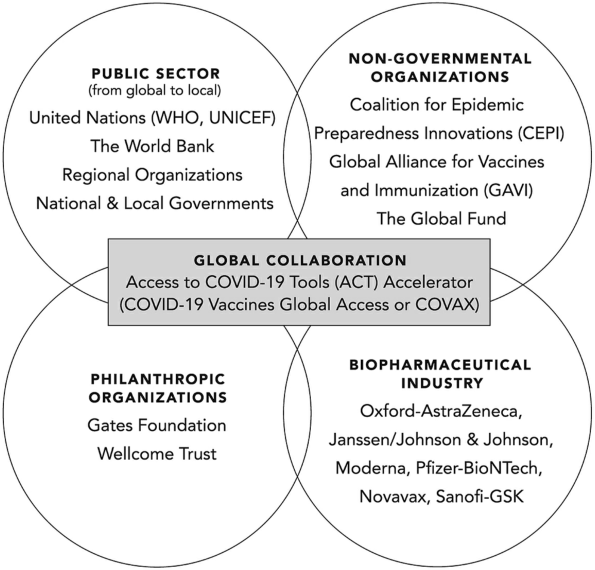
The strategy of prioritizing America’s interests when it comes to vaccines resulted in unforeseen outcomes. Strengthening international cooperation could have produced advantages for both the United States and the worldwide community.
Lesson Nine (Chapter 8: Trust and Confidence Deteriorate)
Effective communication is crucial during a crisis as it plays a vital role in combating misinformation and addressing the breakdown of public trust and confidence. Both the Biden and Trump administrations have been hindered by poor communication, which has further exacerbated the problem.
Lesson Ten (Chapter 11: America the Skilled)
We need to improve in our next attempt. Because there will be another opportunity.
References
2.
The article titled “Crisis Decision-Making at the Speed of COVID-19: Field Report on Issuing the First Regional Shelter-in-Place Orders in the United States” by Aragón TJ, Cody SH, Farnitano C, Hernandez LB, Morrow SA, Pan ES, et al. Is available in the Journal of Public Health Management and Practice [Internet]. It was published in January 2021 and can be accessed via the following link: https://doi.Org/10.1097/phh.0000000000001292.
3.
The article titled “The Urgent Need for Public Health Preparedness Funding and Support” by Hites L, Dyjack D, Atchison C, et al. Can be accessed at https://doi.Org/10.2105/AJPH.2020.306068. It was published in the American Journal of Public Health in March 2021 with the volume number 111 and issue number 3. The page range of the article is 363-5.
4.
The article titled “Facilities Nursing Skilled in Successes of Early COVID-19” by San Francisco et al. Provides valuable insights into the achievements of skilled nursing facilities in managing the COVID-19 pandemic. This article, published in the Journal of the American Geriatrics Society in December 2020, discusses the experiences and strategies employed by skilled nursing facilities to tackle the challenges posed by COVID-19. The authors, including Philip L. San Francisco, Golden A., DuBois HM, Scott J, Stoltey JK, and Louie J, highlight the successes and lessons learned from their research. The article can be accessed at the following link: https://doi.Org/10.1111/jgs.16765.
5.
Louie JK, Stoltey JE, Scott HM, Trammell S, Ememu E, Samuel MC, et al. Comparison of symptomatic and asymptomatic infections due to severe acute respiratory coronavirus virus 2 (SARS–CoV-2) in San Francisco long-term care facilities. Infect Control Hosp Epidemiol [Internet]. 2022 Jan;43(1):123–4.Available from: https://doi.org/10.1017/ice.2020.1371
6.
Lessons from Mass-Testing for Coronavirus Disease in Elderly Long-Term Care Facilities: San Francisco, California, June 2021
Introduction
This is an ongoing book review, and any feedback is welcomed and valued.
For this book review/summary, I watched the following online seminars.
Below is the Index: